
HBOT for Migraines: What the Research Shows
October 20, 2026

Hyperbaric oxygen therapy (HBOT) may help ease pain during an active migraine attack, but the evidence is limited, and there is no reliable proof yet that it prevents future attacks. It is an off-label, investigational use, not a standard migraine treatment. If standard medications have not given you enough relief, it is reasonable to ask whether HBOT belongs in a broader plan. This guide covers what the studies found, what a session involves, who should be cautious, and what to ask before you book.
In HBOT you breathe pure oxygen inside a pressurized chamber. The pressure lets your blood carry more dissolved oxygen than it does at normal air pressure. For decades this has been a mainstream treatment for problems such as decompression sickness, carbon monoxide poisoning and non-healing wounds.
Migraine is a different story. Researchers have long suspected that impaired oxygen use and blood vessel changes in the brain play a role. A systematic review of oxygen therapy in headache disorders describes the theory: oxygen may constrict blood vessels and calm inflammation in ways that interfere with the trigeminovascular pathway, a key driver of migraine pain. It also notes that the field lacks large, multi-center, randomized trials to confirm long-term benefit.
That is the honest starting point. The idea is sound enough to study. The proof is not yet strong enough to call it a standard of care.
The most-cited summary is a 2015 Cochrane review of oxygen and hyperbaric oxygen for migraine and cluster headache. Its main findings for migraine:
| Question | What the review found |
|---|---|
| Does HBOT relieve pain during an attack? | Low-quality evidence of benefit. In pooled data, people given HBOT were far more likely to report pain relief than those given sham treatment (risk ratio 6.21, 95% CI 2.41 to 16.00). |
| Does it prevent future attacks? | No reliable evidence |
| Does it reduce nausea and vomiting? | No reliable evidence |
| Does it reduce the need for rescue medication? | No reliable evidence |
The Cochrane summary rates the evidence as low quality. The wide confidence interval tells you the same thing: the trials were small, so the true effect could be much smaller or larger than the headline number.
Breathing oxygen from a mask at normal pressure is not the same as HBOT. A 2016 randomized crossover trial of 22 adults with migraine tested high-flow oxygen against medical air. At the main 30-minute checkpoint there was no statistically significant difference. At 60 minutes, though, 24% of people on oxygen had pain relief versus 6% on air, and 36% versus 7% had relief of visual symptoms. Exploratory analysis suggested oxygen worked better in moderately severe attacks.
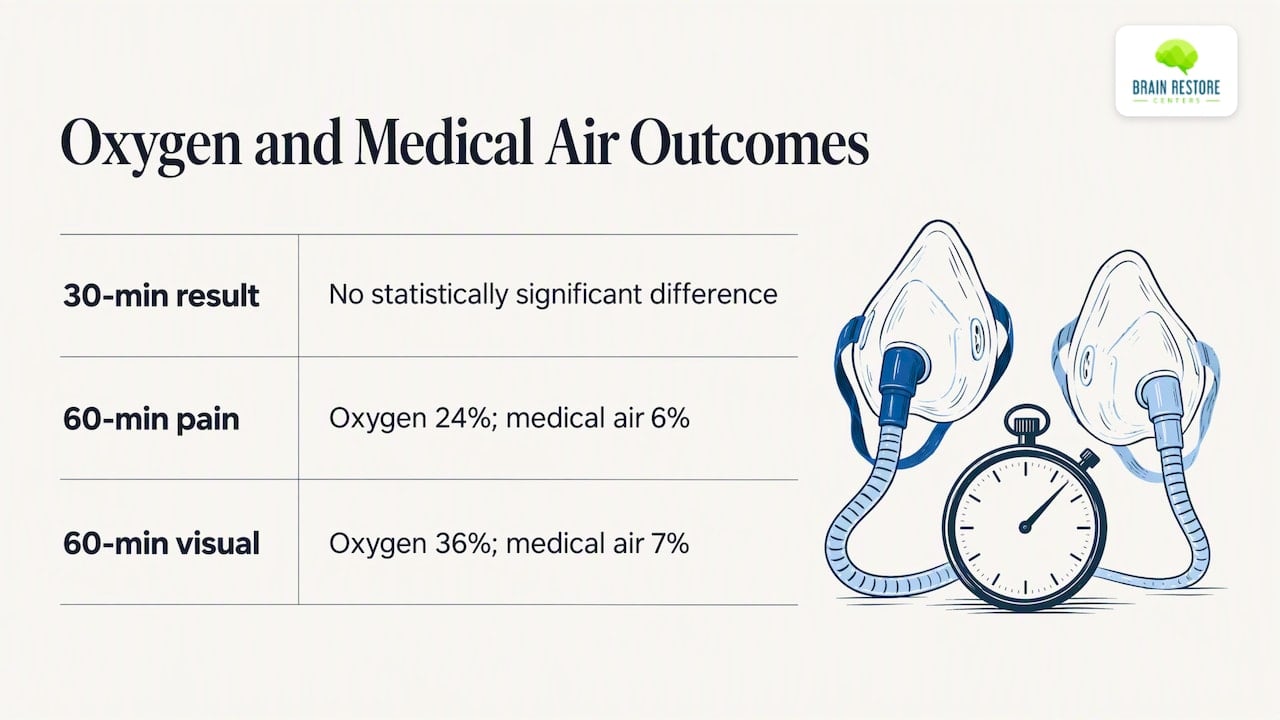
This tells you two things. Results are mixed even in careful studies, and timing and attack severity may matter. Do not read it as proof that a chamber works, because this trial did not use a chamber.
Put the evidence together and a fair summary is this:
You will see claims online that HBOT stops migraines for most people. The research does not support that, and we would rather tell you so now than have you find out after paying for a series of sessions.
No. The Undersea and Hyperbaric Medical Society keeps a list of accepted HBOT indications that includes carbon monoxide poisoning, decompression sickness, diabetic foot wounds and delayed radiation injury. Migraine is not on it. Using HBOT for migraine is considered off-label and investigational, and the same applies to conditions like traumatic brain injury and PTSD.
“Investigational” does not mean “ineffective.” It means the data is not yet large enough to earn official status. For you, the practical effects are:
People who explore HBOT for migraine are most often those whose medications have not worked well, or who want to reduce how much medication they need. That is a reasonable motivation, as long as expectations stay realistic.
Before anything else, get the basics checked. New, sudden or different headaches, headaches with weakness, speech trouble, confusion, fever or a stiff neck, or the worst headache of your life need urgent medical care, not a wellness session. Call 911 or go to an emergency department for those.
A screening also checks for reasons not to use a chamber. Our overview of HBOT contraindications explains that an untreated pneumothorax (collapsed lung) is the one absolute contraindication. Other conditions, such as ear pressure problems, sinus congestion, certain medications and some lung conditions, call for care and a clinician’s judgment. Common side effects of sessions are usually mild, such as ear pressure or fatigue. Tell your provider about everything you take.

Exact protocols vary by clinic and by your health history, but here is the general flow:
If you are wondering how many visits people typically need for brain-related goals, our page on how many HBOT sessions are needed shows what a patient session looks like. Because migraine is off-label, a good provider will agree on a defined trial period with clear checkpoints. You track attack frequency, intensity and medication use, then decide together whether to continue.
At our clinic in Meridian, we see migraine as a signal from a brain and body under strain, not just a pain problem to switch off. When someone comes to us after years of attacks, we want to know what is feeding them. Sleep, blood sugar, hormones, gut health, neck mechanics, stress load and how the brain regulates itself can all matter.
That is why we describe HBOT honestly: a promising, still-investigational option that can sit beside other care. We do not promise it will end your migraines, because the research does not let anyone promise that. What we can do is build a personalized plan, measure what changes, and adjust.
Our team combines chiropractic, functional medicine and brain-based therapies such as neurofeedback and low level laser therapy (photobiomodulation). We bring more than 50 years of combined clinical experience to the table and have earned over 400 five-star reviews, and we use that experience to tell you when something is likely to help and when it is not. If we think HBOT is not right for you, we will say so.
— Chad
HBOT rarely stands alone in a good migraine plan. These are options people often discuss with their care team:
None of these is a guaranteed solution. Together, though, they give you more ways to move forward than any single therapy.
A provider who answers these directly, and who does not promise a cure, is the one to trust.
If migraines are disrupting your work, sleep or family life, we can start with a conversation. Our Brain Restore Program begins with a brain health consultation to look at the whole picture, and hyperbaric oxygen therapy is one of the options we can discuss with you. You can also schedule an appointment in Meridian, or learn more on our main site.
It might help some people. The Cochrane review found low-quality evidence that HBOT can relieve pain during an acute attack. The studies were small, so results are uncertain, and a chamber session is not practical when an attack hits suddenly.
There is no reliable evidence yet that it does. The Cochrane review found nothing solid on prevention. If prevention is your goal, talk with your neurologist or primary care clinician about options with stronger evidence.
Usually not. Migraine is not an accepted HBOT indication, and coverage tends to follow the approved list. Ask your insurer directly, and ask any clinic for a written cost estimate before you start.
For most screened adults it is generally well tolerated, with mild effects like ear pressure being common. Some conditions, including an untreated collapsed lung, rule it out, so a medical screening comes first. Tell your provider about all medications and health conditions.
Questions about your next step?
Our Meridian team can help you understand the evaluation process and which care options may fit your needs.
Schedule a ConsultationPrefer to speak with our team? Call 208-639-1397




