Concussion Dizziness Treatment: What Helps and When
November 17, 2026


Dizziness after a concussion is common, and in most cases it is treatable. For many people it fades on its own within the first one to two weeks. When it does not, the most reliable path is a proper evaluation of why you are dizzy, followed by targeted therapy such as vestibular rehabilitation (exercises that retrain the balance system) or, for a specific inner-ear problem called BPPV, a repositioning maneuver. If you live in the Meridian area and your symptoms have lingered, our Brain Health Consultation is a natural place to start.
You may be reading this because the room still tilts when you roll over in bed, or because a grocery store aisle leaves you off balance. That is frustrating, and it is also a sign your brain and inner ear are asking for a plan, not just more waiting.
Doctors use “dizziness” for several different experiences. According to the Defense Health Agency’s TBICoE fact sheet, it can range from feeling faint or lightheaded to feeling weak or unsteady, to vertigo (the sense that the room is spinning) or being off balance. It can arrive suddenly or be triggered by head movements, and it can last seconds, minutes or longer.
Naming your version helps your clinician. A few questions to ask yourself:
A 2020 review in a peer-reviewed journal points out that post-traumatic dizziness is not one thing. True vertigo, wooziness and lightheadedness on standing can each have a different source, and a careful line of questioning is needed to sort them out.
Your sense of balance depends on three teams working together: the inner ear (the vestibular system), your eyes and your brain, which blends the signals. A concussion can disrupt any of them.
The TBICoE clinical guidance from January 2026 estimates that dizziness follows concussion in roughly 24% to 83% of cases, and potentially up to 90% in the acute phase. Common causes include dysfunction of the peripheral (inner ear) or central (brain) vestibular pathways.
A 2024 TBICoE rehabilitation paper lists several specific culprits:
The same TBICoE guidance notes that other conditions can feed dizziness after a concussion: anxiety, panic disorder and PTSD; heart-rhythm and blood-pressure issues such as orthostatic hypotension; migraine, including vestibular migraine; and sleep problems such as insomnia or sleep apnea. That matters because treating only the inner ear can miss the full picture. If migraine is part of yours, our guide to vestibular migraine treatment explains the options.
The TBICoE fact sheet says many people feel dizzy during the first 1 to 2 weeks after a concussion, and it usually resolves without treatment. A 2022 review by Gianoli estimates that 85% to 90% of concussion symptoms clear within days to weeks. The same review suggests that early resolvers do not need testing, that active treatment should begin if dizziness continues past about 3 weeks, and that problems persisting or worsening at 3 months deserve a deeper workup.
There is no single timeline. If your dizziness is lasting, worsening or getting in the way of work, driving or caring for your family, that is the signal to act rather than wait.
The CDC’s 2024 discharge instructions for mild TBI tell patients to talk to a doctor if they feel unsteady, or if symptoms worsen significantly or do not go away. They also note that dizziness, vision problems or slowed reaction time may mean you need more time off work or school.
The TBICoE guidance calls for immediate referral for:
Any life- or vision-threatening symptom means the emergency department, not an appointment next week. Call 911 if you are in doubt.
The TBICoE guidance describes an evaluation that rules out red flags, takes a history that includes the contributing factors above, and performs a focused physical exam. That exam includes VOMS (the Vestibular/Ocular Motor Screening, a short set of eye and head-movement tasks that reproduce symptoms) and a standard neurological exam. It also confirms you are following a gradual return to activity. If symptoms persist or limit you severely, the guidance suggests a TBI specialty clinic first, when one is available.
Because objective signs may only appear when your head is moved into the provoking position, an exam that actually recreates your symptoms matters. The 2020 review above notes that tests such as the Hallpike maneuver and head-shaking test can be used for this.
For dizziness beyond three months, Gianoli’s review recommends imaging such as MRI to exclude central causes, a full hearing test and a full vestibular evaluation. That is a decision for your physician.
This is the core treatment for lingering dizziness. The TBICoE fact sheet describes it as specialized exercises that help the eyes, inner ear and brain adjust after injury. The goals, as laid out in the Indiana State Department of Health’s mild TBI toolkit, include better gaze stability, better postural control and habituation, which means getting your brain used to a movement that used to trigger symptoms.
Two safety points from the fact sheet:
The evidence is encouraging. A 2023 systematic review found that, for people with dizziness, neck pain or headaches more than 10 days after a sport-related concussion, individualized cervicovestibular rehabilitation may shorten time to return to sport compared with rest followed by gradual exertion. In adolescents with vestibular symptoms, vestibular rehabilitation may shorten time to medical clearance (50.2 days versus 58.4 days in the comparison group). The VA/DoD concussion guideline, as summarized by ASHA, recommends a short-term trial of vestibular, visual and proprioceptive exercises for dizziness after mild TBI, then checking how you respond.
If you want to know what a first visit looks like, read our guide to vestibular therapy for concussion. For a plan matched to a diagnosis, see vestibular exercises matched to your diagnosis.
If your dizziness comes in short, sharp spells when you turn in bed or tip your head back, BPPV is a leading suspect. Gianoli’s review calls it by far the most common inner-ear cause of post-concussive dizziness, found in 10% to 57% of concussion patients. Classic episodes last 15 to 30 seconds and are confirmed with the Dix-Hallpike maneuver, a positioning test done in the clinic. Treatment is canalith repositioning, the Epley maneuver being the most common.
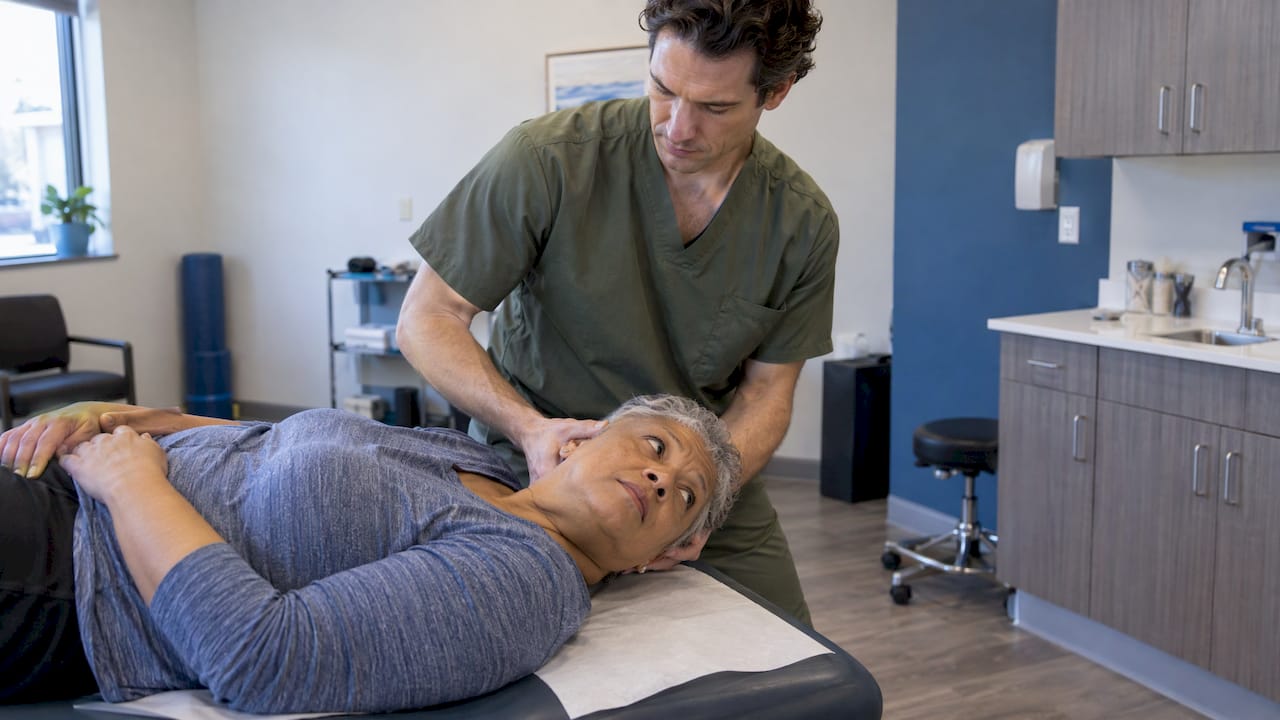
A Barrow Neurological Institute review describes repositioning as highly effective, and notes that traumatic BPPV is more likely to involve both ears (25% versus 2% in BPPV with no known cause). Gianoli adds that post-concussive BPPV more often involves unusual canals, multiple canals and recurrence. In short: get the diagnosis right, and expect that a repeat visit may sometimes be needed. Repositioning should be directed by a provider, as the TBICoE fact sheet also states.
When the neck is a source of dizziness, or when eye tracking is off, treatment targets those systems too. Our guide to clinician-aligned oculomotor exercises walks through the home side of eye retraining, and balance training after concussion covers the balance side and when to seek help.
Sleep, anxiety, migraine and blood pressure changes can each amplify dizziness. Addressing them is part of getting better, not a side issue. If headaches are part of your picture, see how to manage headaches after a concussion. Headaches that show up after exertion are worth understanding too, and this overview of headache after exercise causes explains common triggers and when to be concerned.
The 2024 TBICoE paper reports that early referral for vestibular and oculomotor conditions is associated with quicker return to activity and better outcomes. Gianoli’s review likewise reports significant benefit within 6 to 12 weeks of vestibular rehabilitation when therapy matches the diagnosis. The takeaway is practical: once dizziness passes the first few weeks, a targeted plan beats waiting.
That is also why a multidisciplinary approach makes sense. Dizziness after a concussion often has more than one source: the inner ear, the neck, the eyes, sleep, mood. When one team looks at all of it together, nothing gets missed.
When someone comes to us still dizzy weeks after a concussion, they have usually been told to rest and wait. Waiting helps most people early on, and we want that for you. But if the dizziness is hanging on, you deserve an answer to “why,” not another week of guessing.
Our approach is built around the whole person: your brain, your balance and your body, in one place. We offer neurofeedback, progressive focused rehab, low level laser therapy, chiropractic care and hyperbaric oxygen therapy, and our team brings over 50 years of combined clinical experience to each plan. Our goal is a personalized plan that helps you reclaim your steadiness and your confidence, at a pace your brain can handle.
You do not have to push through it alone. Start with a conversation about what you feel, when it happens and what you want back in your life.
Chad
If you are in Meridian, Idaho or the surrounding Ada and Canyon County area and your dizziness has not cleared, our Brain Restore Program begins with a Brain Health Consultation. It is where we listen to your story and map out next steps for cognitive, neurological and balance concerns after a concussion.
You can learn about all of our services on our home page, or book an appointment when you are ready. Clinic patients also tell us that 400+ five-star reviews were part of why they felt comfortable reaching out.
For many people it fades within the first 1 to 2 weeks without treatment, according to the TBICoE fact sheet. If it continues past about 3 weeks, active treatment is reasonable, and persistent or worsening dizziness at 3 months calls for a deeper evaluation.
It depends on the cause. Vestibular rehabilitation is the main treatment for lingering dizziness and balance trouble, and canalith repositioning treats BPPV. Neck, eye, sleep and migraine factors are treated alongside. Ask your provider to confirm any exercises are safe for you first.
Brief increases during vestibular exercises can be expected, and they should settle within a minute after each set. If they do not, stop and try again the next day. If symptoms are getting worse overall, talk to your doctor before continuing.
Go to the emergency department for sudden hearing loss, double vision, unequal pupils, sudden vision loss or visual-field loss, or persistent bleeding or drainage from the ear or nose. These are the red flags in the TBICoE guidance.
Questions about your next step?
Our Meridian team can help you understand the evaluation process and which care options may fit your needs.
Schedule a Brain Health ConsultationPrefer to speak with our team? Call 208-639-1397